
Patient Intake Form
For clinics and private practices registering new patients before a first appointment. Send it ahead of the visit so patients complete it at home and arrive with fewer clipboard minutes.
- Fields
- 73
- Pages
- 3
- Paper
- Letter
Fill it online without an account. The blank PDF is free to download and works in any PDF reader. Downloading a filled copy from the editor needs a free account — 3 downloads a month, no watermark. See plans
Reviewed
Before you start
What you need to fill it in
- Patient's legal name, date of birth and contact details
- Insurance card (front and back) with member and group numbers
- Emergency contact
- Current medications with doses
- Known allergies and reactions
- Primary care physician and pharmacy
What's inside
73 fields, ready to fill
- 46Typed answersnames, addresses, descriptions
- 4Dateschecked as real dates
- 22Choicescheckboxes, options, dropdowns
- 1Signaturessignature and initials
16 required — the editor counts down how many are left while you fill.
Instructions
How to fill out the Patient Intake Form
- 1
Patient details
Enter your legal name as it appears on your insurance card, date of birth, sex assigned at birth if your clinic asks, and contact details.
- 2
Insurance
Copy the plan name, member ID and group number from your card. If the policyholder is someone else, enter their name and date of birth.
- 3
Reason for visit
Describe your main concern in a sentence or two and how long it has been going on.
- 4
Medications and allergies
List every prescription, over-the-counter drug and supplement with the dose. List allergies and what happens when you are exposed.
- 5
Health conditions
Check any conditions you have been diagnosed with and add details.
- 6
Consents and signature
Read the consent, financial and privacy statements, check each box and sign.
Fill it online
What filling it looks like
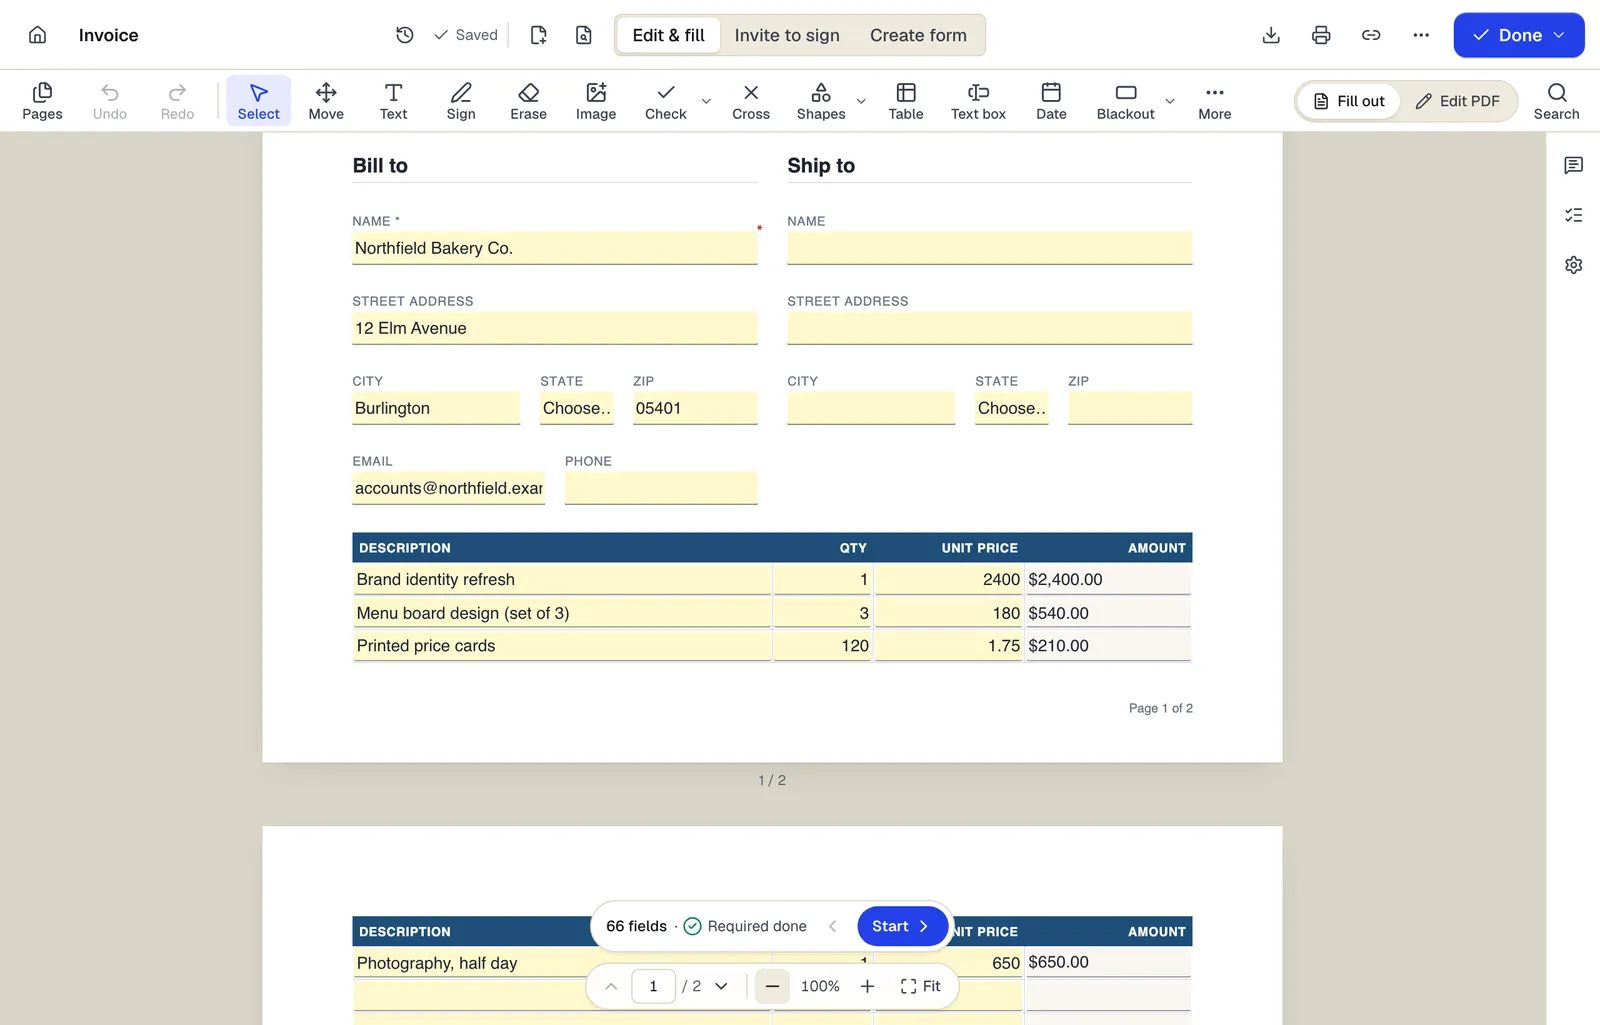
- Edit & fill, Invite to sign and Create form are three modes of the same editor
- Amounts are formula fields: they calculate as you type
- The field navigator counts what's left and jumps to the next field
Shown with our invoice template. Sample content; names are fictional.
Written for: General (US)
This template is a general starting point, not medical or legal advice. HIPAA, state privacy and consent rules vary; have your compliance lead or a qualified professional review it before use.
Written by PDFBetter and last reviewed October 15, 2026. Spotted a problem? Tell us.
Patient Intake Form: questions people ask
Is it safe to fill this form online?
When you fill a PDF in PDFBetter, the file is processed according to the tool you use. For forms with health information, practices should use a workflow their compliance team has approved; PDFBetter is not a HIPAA-certified service.
Can a parent fill it for a minor?
Yes. The parent or legal guardian enters the child's details as the patient and signs as the responsible party, stating their relationship.
Does the practice need my signature on the privacy notice?
HIPAA requires providers to make a good-faith effort to get written acknowledgment that you received the Notice of Privacy Practices. You can still be treated if you decline to sign.
What if I don't know my medication doses?
Write the name and bring the bottles or a pharmacy printout to the appointment.
Can clinics customize the conditions list?
Yes. Open the template in the editor or form builder to add specialty-specific questions.
Ready when you are
Fill the Patient Intake Form now — no account to start.